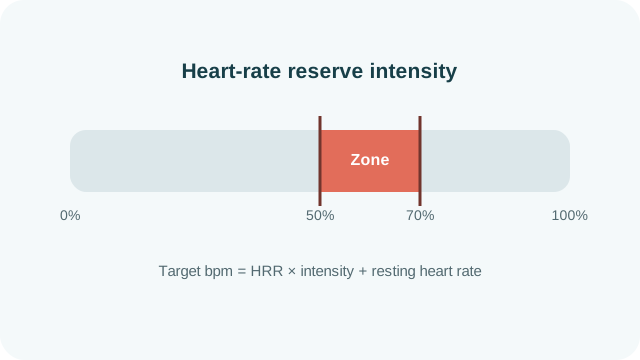
Read the outputs as estimated points on a continuum, not exact boundaries between safe and unsafe effort. Day-to-day heart rate changes with sleep, hydration, temperature, stress, caffeine, and accumulated fatigue.
The familiar 220 − age equation has substantial individual error. A measured maximum from an appropriately supervised test may differ. Do not attempt an all-out test solely to replace this estimate without considering health status and professional guidance.
The reserve method includes resting pulse, so two people of the same age can receive different targets. A falling resting pulse may reflect training adaptation, but measurement conditions and health also matter.
Heart-rate monitors can lag or misread, particularly wrist sensors during rapid movement. Pair the number with how the effort feels and, where appropriate, the talk test. The American Heart Association describes moderate and vigorous zones as broad percentages of maximum heart rate; those are a different method from reserve percentages.
Beta blockers and other medicines can blunt or alter heart-rate response. People with cardiovascular, pulmonary, metabolic, or other relevant conditions should use targets supplied by a qualified clinician or rehabilitation team.
Beginners commonly start near the lower end and progress gradually. Session duration, frequency, activity type, recovery, and symptoms matter as much as a single pulse reading.
The page’s “light,” “moderate,” and “intense” labels are convenient labels for its three points. They should not be treated as a clinical classification. Record the formula used when comparing results from another source.
Use the same resting measurement method when tracking change over time. Sitting versus lying down, manual pulse counting versus a device, and different counting intervals can shift the value. An unexpected persistent change deserves context and, when concerning, professional advice.